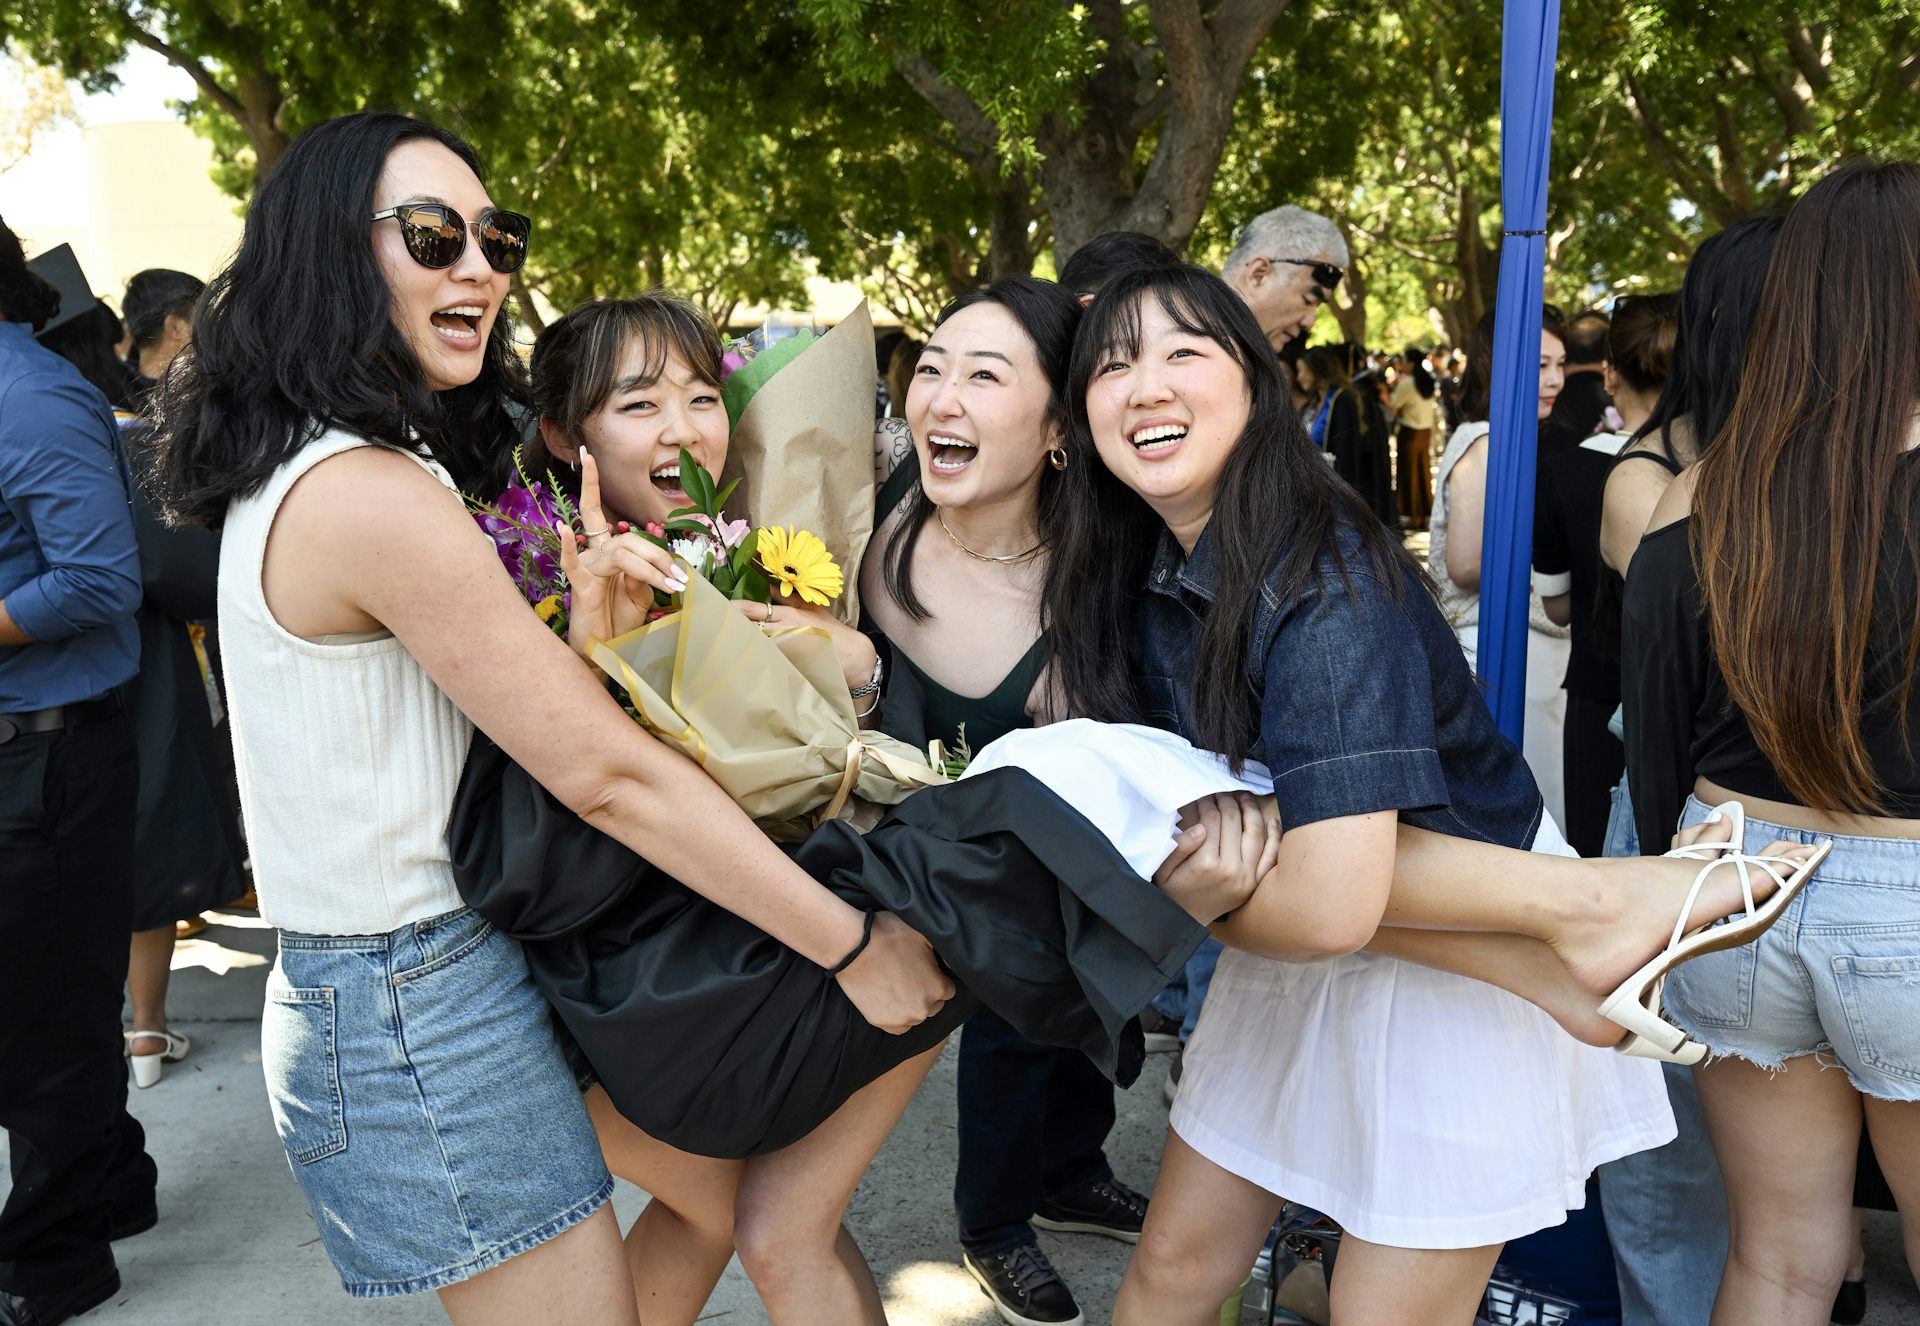By age 18, my knees hurt. I didn’t know why, and they didn’t hurt a lot, but they did hurt a bit most of the time. As someone who took a lot of dance classes and played my share of netball, it was annoying, but not something I thought much about. After all, I reckoned, bad knees run in my family. But by age 20, the pain had gone from a bit annoying to definitely annoying. I decided, for the first time, to see a doctor about it.


She was a brisk woman with close-cropped grey hair, who glanced at me and told me my knee pain was due to early-onset arthritis as a result of my being overweight. My blood tests were negative for rheumatoid arthritis — but that didn’t matter, she told me. The only way to stop my pain from getting worse was by losing weight. So with the resigned sigh of anyone who has grown up fat, I accepted my fate. I was arthritic, at 20.

By 22, things were worse. My knees had gone from hurting a bit most of the time to spontaneously collapsing in blinding pain while I was doing innocuous activities like walking down the street. I went back to the doctor — a different one, because I just saw whoever was available at the student clinic. He asked me about my pre-existing medical conditions. I explained that my arthritis was a result of being overweight. He looked at me incredulously. “That’s not a thing.” No one gets non-rheumatoid arthritis in their twenties as a result of being overweight, he explained.

Instead, he decided we should figure out exactly why my knees were spontaneously collapsing. He sent me for an MRI, and I had a consultation with a specialist surgeon. “Patellae chondromalacia,” the surgeon declared. He showed me the shadows on my scan, which indicated rough patches on my knee caps. It was probably hereditary, exacerbated by my weight.

“Ok,” I said. “So what can I do about it?”

“You’re just going to have to manage the pain,” he explained. “And once it gets to be too much, you’re going to need your knees replaced. And that will probably be before you’re 30.”

[quote position=”full” is_quote=”true”]I had eight years before I turned 30. It felt a bit like a death sentence.[/quote]

Resigned, I accepted my diagnosis. I said goodbye to yoga and dance, which aggravated the condition, and started wondering about how much two new knees might cost, and how I’d get around on crutches. I had eight years before I turned 30. It felt a bit like a death sentence.

At 24, my new housemate decided she was joining our local gym, and in a moment of optimism, I decided to go with her. This gym offered a free short session with one of their personal trainers to help newbies learn the ropes. “I’ll put you with Hao,” the receptionist said. “He’s got a physio background; he’s good with injuries.”

Hao was intimidating — really tall, super buff, thick Chinese accent that was hard to understand at first. “It says here you’ve got an injury,” he told me. “What is it?”

“I’ve got patellae chondromalacia in both knees,” I replied. “It’s-“

“Oh that,” he said, interrupting me. “I can fix that.”

What?

Hao explained to me that what I had was a pretty standard sporting injury that is usually treated successfully using exercise — a fact that none of my doctors had mentioned. I’d probably injured myself as a result of all that dance and netball I did as a teenager, and it might have been exacerbated by my family history of dodgy knees. It’s normally caught early and treated early — it’s very rare for it to get to the point of causing knees to collapse, but that can happen in serious cases with no treatment. “Work with me for 10 sessions,” said Hao. “If you don’t notice a difference, I’ll give you your money back.”

Well, after 10 sessions I noticed a pretty significant difference. After six months, the pain that had plagued me for six years was entirely gone.

[quote position=”full” is_quote=”true”]When doctors looked at me, they didn’t see a girl who danced, cycled, and played team sports. They saw a fat girl .[/quote]

I can’t help but think that there’s a whole lot of physical pain I could have avoided if any of the medical professionals I saw had considered the fact that I might have a sporting injury. And I can’t help but wonder if the reason they didn’t has to do with my weight.

When doctors looked at me, they didn’t see a girl who danced, cycled, and played team sports. They saw a fat girl — and they based their diagnosis on stereotypes about what that meant. I’m 29 now, and my knees no longer hurt. I don’t need to have them replaced — but if I’d listened to the weight-prejudiced opinions of my doctors, I might have.

This story is hardly unique.

Research shows that doctors have less respect for patients with higher body-mass indexes, which can lower the quality of care those patients receive. As one study put it:

“Many health care providers hold strong negative attitudes and stereotypes about people with obesity. There is considerable evidence that such attitudes influence person-perceptions, judgment, interpersonal behavior, and decision-making. These attitudes may impact the care they provide.”

Troublingly, many of the ideas that doctors have about fat patients aren’t even grounded in medical fact. Indeed, too often it’s forgotten that the science around weight loss and health isn’t all that settled. Does excess weight cause you to live a shorter life? Maybe, maybe not. Countless studies by BMI category have found that overweight people actually have lower rates of all-cause mortality than normal weight people.

Some researchers think that if you adjust for the increased risks caused by weight cycling (aka. yo-yo dieting) and dangerous weight-loss drugs, you’d find the same mortality rates for normal, overweight, and obese people — yes, even very obese people. And even without the adjustments, the increased risk for very obese people is only small — not the “you’ll be dead before you’re 30” nonsense often pedaled by purveyors of weight-loss surgeries.

What about serious disease? There’s certainly a correlation between being overweight and some diseases, but multiple studies suggest that the weight might actually be a symptom rather than a cause.

Then there’s the idea that excess tissue “strains” the body. Eminent obesity researcher Dr. Paul Ernsberger has been quoted as saying, “The idea that fat strains the heart has no scientific basis. As far as I can tell, the idea comes from diet books, not scientific books . . . Unfortunately, some doctors read diet books.”

[quote position=”full” is_quote=”true”]So why, then, do doctors insist on prescribing diets and weight loss as a treatment for anything and everything?[/quote]

What about dieting? Well, there actually is some scientific consensus there :  Diets don’t lead to lasting weight loss—not even if you call them lifestyle changes. After an extensive metastudy of diet and weight loss studies, Dr Traci Mann concluded, “The benefits of dieting are simply too small and the potential harms of dieting are too large for it to be recommended as a safe and effective treatment for obesity.”

So why, then, do doctors insist on prescribing diets and weight loss as a treatment for anything and everything?

Sarah, 29 from Newcastle, Australia, had the misfortune of breaking both legs as a teenager, the result of a freak accident involving her legs falling asleep and then getting twisted to the point of breaking. Not long after learning how to walk again, she was involved in a serious car accident that left her with further damage to her legs. “I’m accident-prone,” she laughs. The multiple injuries have left Sarah with a build up of scar tissue that can make walking painful. But when she went to the doctor, her pain was blamed on her weight.

“My weight is a factor in the healing process,” she says, “But it wasn’t the cause of my injuries — and I’ve got police reports, x-rays, and specialist reports to prove it.”

Sarah changed doctors recently, and her new doctor decided to do a full medical history, checking the notes from all the physicians Sarah has seen. What she found shocked her. “She said there’s no record of my injuries with most of my previous doctors,” Sarah said. “They all had written that my leg pain was caused solely by my weight, and that meant I wasn’t getting any useful treatment for the pain. They just told me to diet.” Sarah’s new doctor promptly started her on a physical treatment plan designed for someone with compound injuries and severe internal scarring.

The difference has been immediate.

“Within two weeks I could walk nearly five kilometers. Before I started the treatment, I could only manage one kilometer or less before my knees were so swollen and painful that I couldn’t keep going,” said Sarah. “Getting actual treatment for my injuries, rather than just being told to lose weight and see what happens, has changed everything.”

Just to be clear, I’m not saying that eating healthily and exercising aren’t good for you. The problem is when doctors prescribe diets and weight loss to patients without fully considering their symptoms and other treatment options.

Stigmatization may also, problematically, stop fat people from seeking out medical care in the first place.

“I just don’t go to the doctor,” says Anita, a 28-year-old advertising executive. The last time Anita saw a doctor, it was a routine visit to discuss vaccinations and antimalarial medication for an upcoming overseas trip. The doctor prescribed the vaccines and asked a nurse to administer the jabs. It was the nurse who decided Anita had diabetes — without having spoken to her, or seeing anything pertaining to her medical history.

“He kept saying I would get a discount on the vaccines if I registered my diabetes,” Anita explained. “I haven’t got diabetes, but he wouldn’t listen. His whole attitude was like, ‘You know you’re fat, right?’ Um, yeah, I’ve noticed that, actually. Just give me the jabs.” The experience was pretty upsetting, and left Anita firmer in her resolve to avoid doctors wherever possible.

Still, Anita, Sarah, and I are relatively lucky; our experiences have caused us pain and humiliation, but no permanent damage. This is not true for everyone.

First Do No Harm is a website that chronicles the experiences of fat people with medical professionals — and it’s filled with harrowing stories.

One woman lost a lot of weight suddenly and was praised for it — with doctors missing the fact that it was a sign of the cancer that shortly killed her.

A man vomited constantly due to multiple sclerosis, but instead of viewing that as a medical red flag, doctors simply celebrated the 120-pound weight loss it caused. The vomiting led to permanent nerve damage, back pain, and tooth decay.

A woman had an emergency doctor declare that she didn’t need treatment for abdominal swelling after a serious car accident because she was just fat. She nearly died.

A woman went years just being told to lose weight to address her ongoing, multiple health problems. It turns out she has a rare neurological disorder; the diagnosis delay has led to permanent brain damage.

There’s another trove of awful stories on fat prejudice here. And of course Google’s got plenty more.

[quote position=”full” is_quote=”true”]Hormonal problems? Lose weight. Broken finger? Lose weight. Migraines? Lose weight.[/quote]

A consistent narrative runs throughout these stories. Hormonal problems? Lose weight. Broken finger? Lose weight. Migraines? Lose weight. Losing weight is the consistent — sometimes only — treatment offered for every ailment imaginable.

For many, changing the narrative around weight is literally a matter of life or death. So what can be done to address the problem?

The good news is that there’s some recognition within the medical profession that this is a serious issue which must be addressed. It’s been noted that medical students don’t receive nearly enough training on obesity, and efforts are beginning to try to change that. Researchers are also working on empathy programs and raising awareness about the impact of implicit bias against patients. All of this is a promising start.

At the same time, we can all become our own health advocates. If you’re a fat person, or someone you care about is a fat person, you can develop your critical thinking skills and challenge the classic “just lose weight” prescription if it doesn’t seem to fit the symptoms.

This isn’t easy. There’s an implicit power imbalance between patient and doctor that makes challenging their statements very difficult. By working to become experts on our own health and our own situation, we stand a better chance of being able to call out something that doesn’t feel right.

Doctors are highly educated people, but they’re subject to the same biases as the rest of us, and many of them don’t stay up to date with the latest research. That’s not good enough. If obesity really is a major health concern, it’s essential that doctors stay educated on recent studies and metastudies that look at how to get the best outcomes for fat patients. If doctors really do care about their patients, they need to start looking at the overall picture of a person’s health, not simply the size of their body.

Most of all, doctors need to stop prescribing a treatment that’s proven not to work for conditions that don’t warrant that treatment in the first place.

The medical profession needs to step up. It needs to accept that diets aren’t the universal treatment option for fat people. It needs to accept that fatness isn’t the universal cause of ill health in fat people. It needs to engage with the very real damage caused by its attitudes toward fat people, and with the substandard care delivered to many people as a result of their size.

It’s not exaggerating to say that lives depend on it.

This piece is published in partnership with The Establishment.

  • Your cells keep a record of every workout you’ve ever done – and those gains persist even after a break from exercise
    Photo credit: Williams+Hirakawa/The Image Bank via Getty Images – Your body retains the benefits of exercise even when you need to hit pause.
    ,

    Your cells keep a record of every workout you’ve ever done – and those gains persist even after a break from exercise

    New research suggests muscle and liver cells retain a memory of exercise, offering hope when injury or life interrupts a workout routine.

    Have you ever taken months off training – maybe due to an injury, a new baby or crushing work deadlines – and come back convinced you were starting from zero?

    Research from our team has some good news: At the cellular level, you probably weren’t.

    We found that muscle and liver cells store memories from every training session in ways that may help improve endurance, control blood sugar levels and even slow weight regain after inactivity.

    Use it or lose it? Maybe not

    For most of the past century, long before fad diets and fancy workout trends took off, exercise was considered one of the most effective lifestyle changes to lower the risk of heart disease, Type 2 diabetes, several cancers and early death for people of all ages. But people typically understood exercise as something whose beneficial effects fade away over time: You use it or lose it.

    When you stop training, your maximum oxygen uptake, muscle gains and insulin sensitivity drift back to where they started, often within weeks. Physical activity guidelines are built on this fact, which is why they emphasize consistency above all else.

    Consistency, however, is a luxury that roughly 3 in 4 American adults aren’t able to enjoy. People can experience injuries, illness, pregnancy or jobs that limit their time for or ability to exercise. If adaptation really resets, every time you step into the gym would be as if you’ve never been there before. But that scenario doesn’t match what coaches and returning athletes typically describe: In practice, people who have trained before can get fit again faster than those who haven’t undergone similar training.

    In recent years, however, scientists have started challenging the concept of “use it or lose it.” New research hints that your cells might keep a record of your training history so all of your gains are not completely lost.

    More than muscle

    We are exercise physiologists who study how cells remember exercise. Our lab and others have shown that the body is able to store a form of exercise memory across different organs.

    To study how this exercise memory works, our team of researchers use an ON-OFF-ON exercise training protocol in mice, which involves an initial four- to eight-week training period, followed by detraining – a period of no exercise – and a second training bout. This method allows us to examine how cells form a memory of exercise, maintain a record of exercise through detraining, and recall memories of prior training when exposed again to exercise.

    Using this strategy, our team found that skeletal muscle memory accelerates muscle growth. Compared to mice with no training history, mice who retrained grew bigger muscles, and the individual muscle fibers inside those muscles grew too. Larger muscle fibers meant that the working cells were themselves getting bigger, rather than the surrounding tissue.

    Looking more closely at these muscle cells, we found that retrained muscle is better at matching energy production to demand – meaning, the muscles were better at drawing from energy stores when it’s needed most – and this ability persists without further exercise. This memory held even when the mice ate a high-fat diet, suggesting that prior training can still offer benefits even when diet is working against those gains.

    Muscle isn’t the only body part that learns from exercise. Working muscle needs fuel, and the liver supplies it during and after training sessions.

    My colleagues and I found that liver cells also store exercise memory and uses it to feed muscle more efficiently. In both mice and people who trained, stopped, then trained again, their livers released higher levels of a family of enzymes called carboxylesterases. These enzymes chop up lipids circulating in the blood, delivering fat in a form that muscle can take up and burn as it grows.

    A record that outlives you

    Recorded cellular memories of exercise may even be passed down to future generations.

    In mice, we found that three to four weeks of maternal and paternal endurance exercise can have a lasting effect on their offspring. Compared to offspring born to sedentary parents, parental exercise granted protection against poor blood sugar levels and excess weight gain for an entire year after birth.

    Researchers have hypothesized numerous ways that prenatal exercise may affect offspring. For example, maternal exercise might allow offspring to spend more time developing in the womb or lead parents to producer higher quality milk.

    But there remains much to be discovered on how parents influence the health of their children and whether their lifestyle could provide a fitness advantage across generations.

    Every cell remembers

    Biology has traditionally granted memory to a short list of cells. Neurons store memory in the connections between them. Immune cells store memory so they can recognize pathogens faster and more strongly the next time they encounter them.

    Researchers previously considered all other cells to be memoryless; a cell responds to a signal, then returns to baseline without keeping a record of that interaction. But that assumption is now coming apart.

    Skin stem cells can keep a record of inflammation, allowing them to heal a new wound faster months later. Human fat cells keep a record of obesity that persists even after substantial weight loss, which may account for why you gain weight faster when switching back to a high-calorie diet – the so-called yo-yo effect.

    We propose that every cell in the body remembers exercise, regardless of how little or how much someone trains. The question is how long these records are stored and whether researchers could prolong or expand each cell’s storage capacity. Better understanding of how cells learn and remember exercise, where they store memories and how those memories are preserved could help improve exercise guidelines for those who cannot exercise for prolonged or consistent periods of time.

    To be clear, none of these findings are evidence for skipping the gym; nothing in our data suggests the effects of past training can substitute for present training. But there is hope that the work you put into getting in shape isn’t completely lost over time.

    Somewhere, deep in your cells, there is a record waiting to be replayed the next time you lace up your running shoes, pick up a pair of dumbbells or want to fulfill a New Year’s resolution.

    This article originally appeared on The Conversation. You can read it here.
  • Friendship is built over time, through ordinary moments – I teach lonely college students to notice them
    Nearly 6 in 10 college students said in 2026 that they felt lonely sometimes or always. Denis Novikov/iStock/Getty Images Plus
    ,

    Friendship is built over time, through ordinary moments – I teach lonely college students to notice them

    A college course explores how small, everyday interactions grow into lasting connections.

    Professor of Political Science and Director of the Center for Applied Civic Leadership, Coastal Carolina University

    The first skill I learned when I became a political science professor nearly 20 years ago was how to quiet a room full of chatty undergraduates.

    These days, I often walk into a silent room, with students staring at their phones and barely acknowledging the classmates beside them.

    As I read more about the United States’ loneliness crisis, I began noticing a version of it among my students.

    In a 2026 national survey of over 40,000 college students, nearly 6 in 10 said they felt lonely sometimes or always. At the same time, federal time-use data show that the share of Americans who socialized in person with family, friends or others on an average day fell from 38% in 2015 to 30% in 2025.

    Those and similar other studies capture a familiar contradiction seen on college campuses like my own: Many new students want close relationships, but feel anxious about initiating them and have had little practice sustaining them.

    I realized that my students rarely spoke to one another, and went entire semesters without learning their classmates’ names. Many students seemed unsure how to cross the few feet between them and their peers and make the social connection they craved.

    I designed a freshman honors seminar, “Friendship & Society,” around this uncertainty, combining the academic study of friendship with practical exercises in forming and sustaining it.

    Two women walk closely together down a stone path with red brick pillars on either side of them.
    College students in this class learn about how positive social interactions activate the brain’s reward system while isolation triggers a stress response. Klaus Vedfelt/Digital Vision via Getty Images

    Understanding friendship

    In this course, students examine how an initial exchange can develop into friendship through repeated contact and shared time, and why many potential connections never progress into a lasting friendship.

    They consider how friends help shape identity and memory, whether old friends are owed continued loyalty after their lives diverge and whether a friendship can remain meaningful after it ends.

    Students also look at how friendship can have strong effects on physical and mental health, making it what I believe is an overlooked public health issue. Friendships can also help shape people’s broader sense of belonging in a community, building the social trust that civic life depends on.

    Students test those questions through 10 “Friendship Practices,” a series of experiential activities I designed. Students are asked to share a meal with classmates or visit a public gathering place like a café or lounge to see how these settings can encourage conversation. During a “friendship safari,” small groups walk across campus, noting where conversations begin and where students pass one another without speaking.

    In private journal entries and submitted reflections, students record what they expected from each situation, and what happened when they tried to form connections. They make a short film telling a story of friendship on campus and end with a friendship memoir tracing how their own relationships and expectations changed during their first semester of college.

    Diving into friendship

    Students read “Stay True,” a memoir about a friendship between author Hua Hsu and his classmate Ken that shapes Hsu’s sense of himself long after his friend’s death.

    Neuroscientist Ben Rein’s book “Why Brains Need Friends” explains the biology of connection and isolation, and shows how positive interactions activate the brain’s reward system while isolation triggers a stress response.

    Students also read longform journalism, social science research, public health reports and political philosophy on aspects of loneliness. They also watch TED Talks and films that explore how a brief encounter with a stranger can, over time, become a friendship.

    Lessons learned

    Students learn that a friendship is built from countless moments that may feel meaningless while they are happening. An unremarkable meal, or a conversation that fills 10 spare minutes rarely feels consequential on its own.

    Over time, those moments build relational capital, meaning the shared trust and history friends can draw on when life becomes difficult or a disagreement needs repairing.

    That reserve reaches beyond a single relationship. Communities become more connected when people have accumulated enough ordinary experience together to trust one another and keep showing up.

    Four young women smile and pose as they lift one of the women, wearing a black graduation gown and carrying flowers, in the air.
    Individual, ordinary moments with peers over time can build and help form a friendship. Jeff Gritchen/MediaNews Group/Orange County Register via Getty Images

    By the end of the course, students can weigh different kinds of evidence about how friendships form, develop and sometimes fade. They also become better able to start a conversation, recognize which public spaces make it easier to meet and spend time with others, and identify habits that help relationships deepen over time.

    They finish with a clearer sense of how relationships take shape and how their own choices contribute to the communities forming around them.

    Uncommon Courses is an occasional series from The Conversation U.S. highlighting unconventional approaches to teaching.

    This article originally appeared on The Conversation. You can read it here.

  • Pope Leo XIV’s lung cancer highlights growing number of nonsmokers diagnosed with the disease – and younger people too
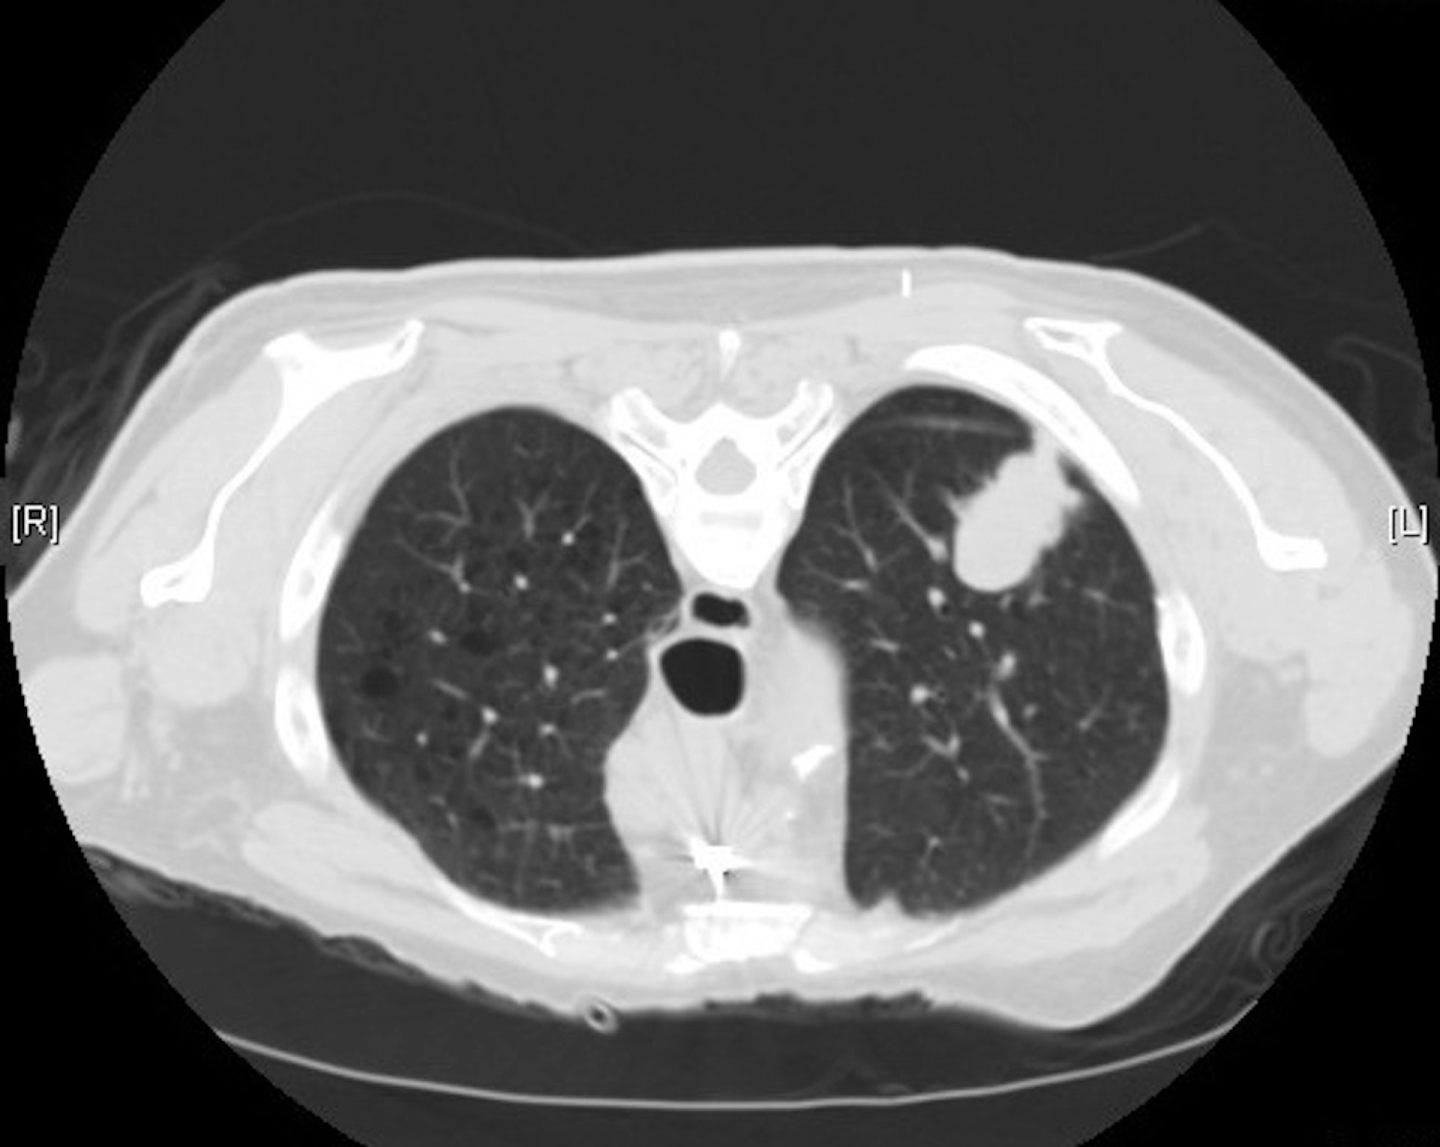
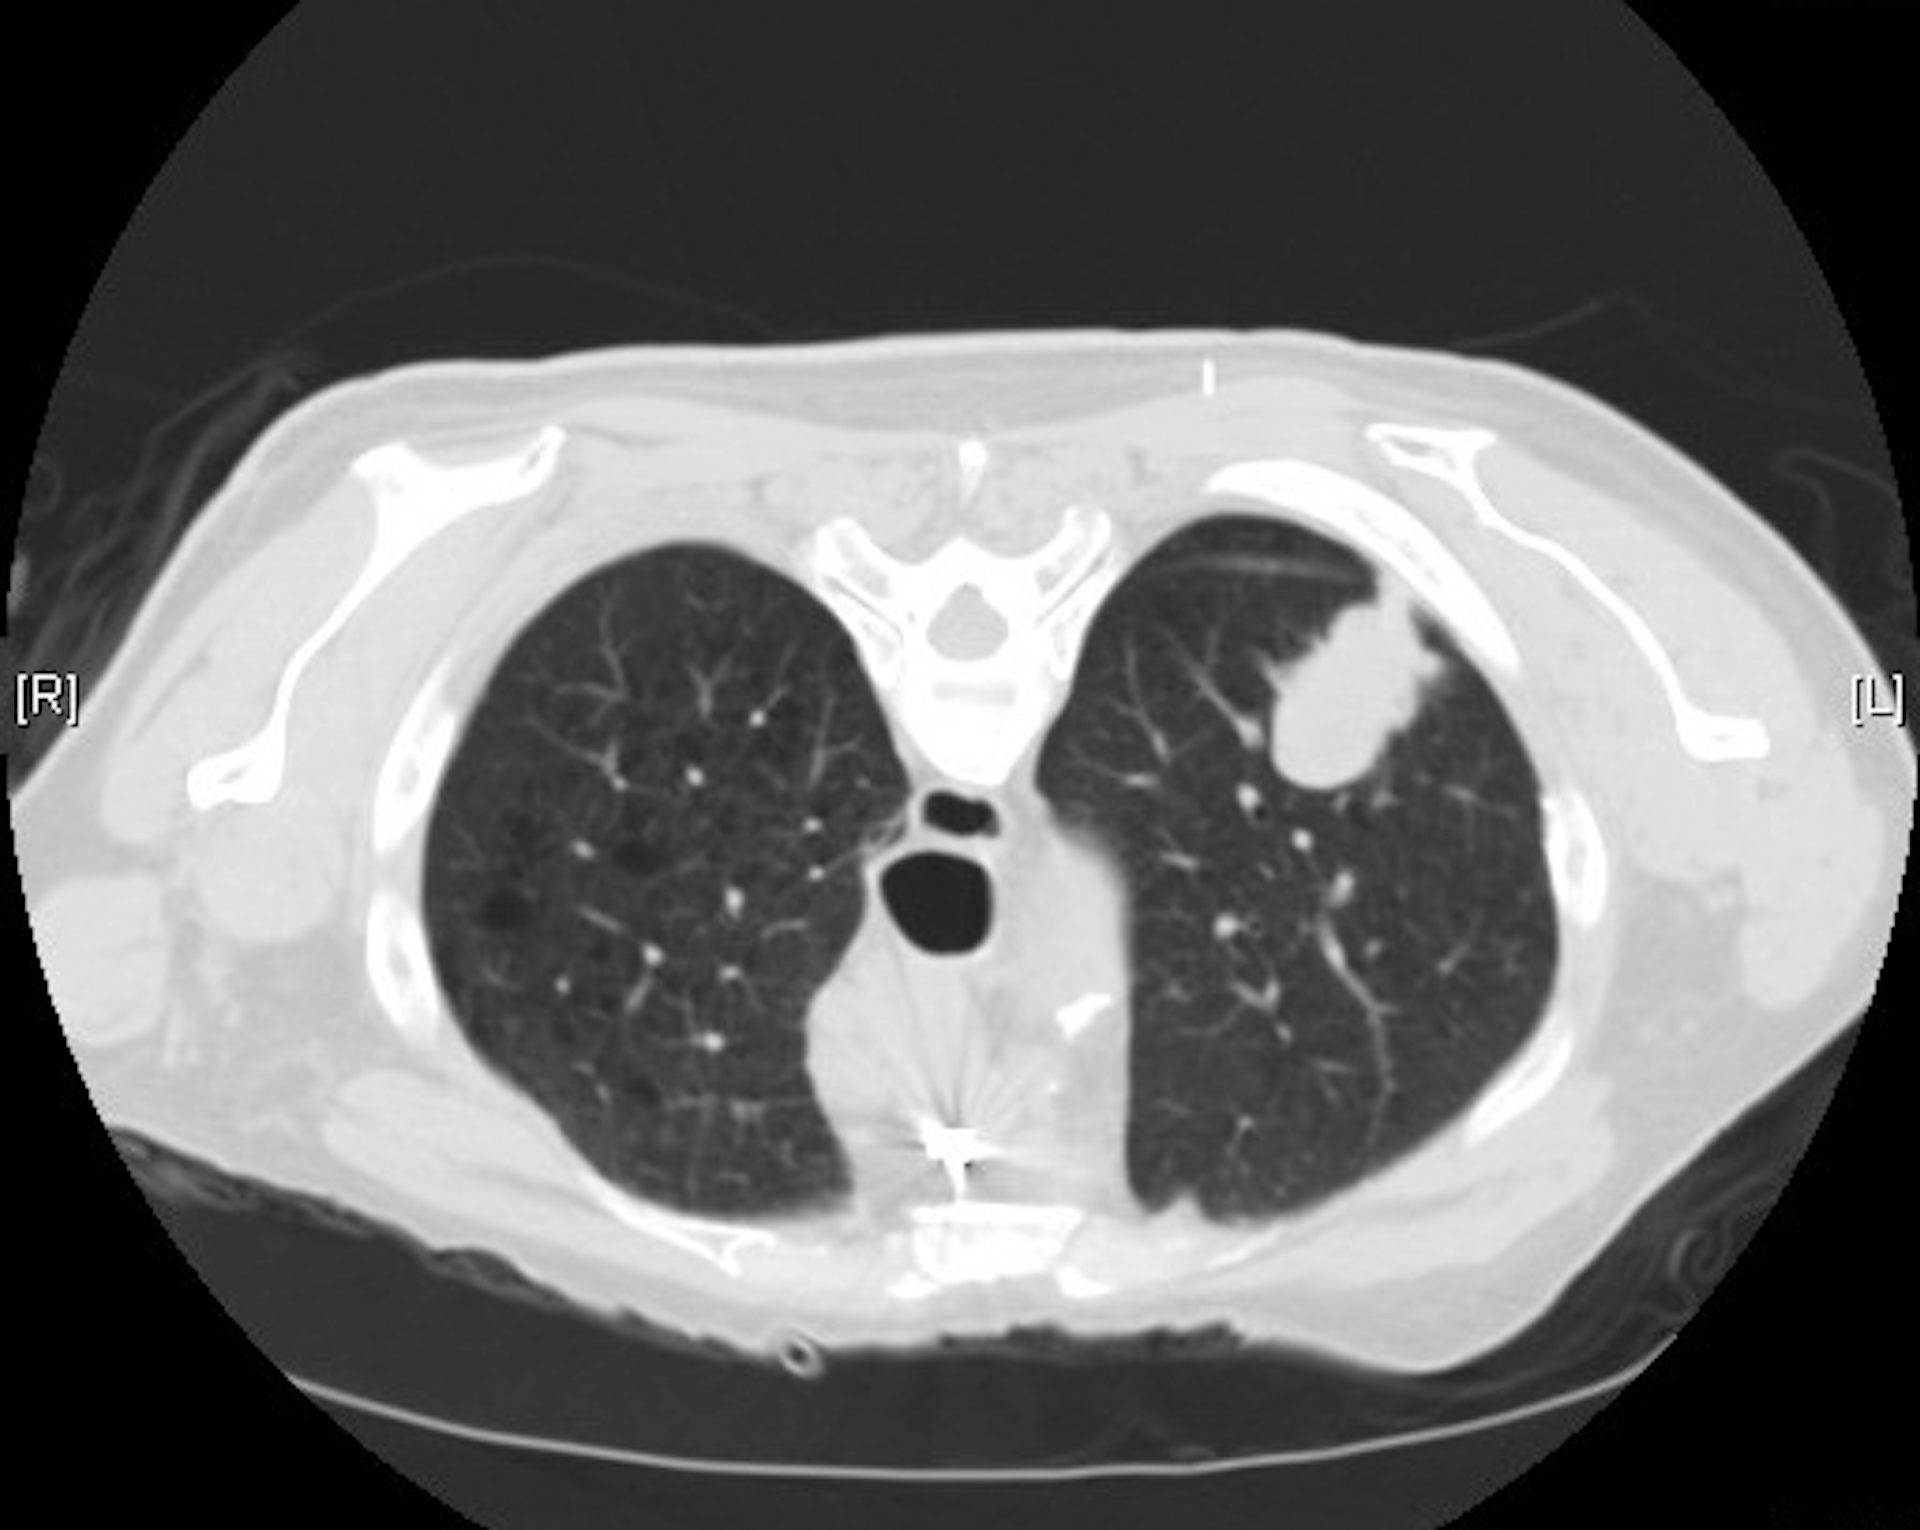
    A low-dose CT scan can help with early detection of lung cancer. In this image, the tumor is the white nodule in the upper right corner of the black space. Atlas of Pulmonary Pathology/Flickr, CC BY-SA
    ,

    Pope Leo XIV’s lung cancer highlights growing number of nonsmokers diagnosed with the disease – and younger people too

    Smoking isn’t the only risk factor, and screening can miss those who never smoked.

    When many people think of an average lung cancer patient, they often imagine an older man smoking. But the face of lung cancer has changed. Over the past 15 years, more women, never smokers and younger people are being diagnosed with lung cancer.

    In fact, lung cancer is the leading cause of cancer death among women, and more women die from lung cancer than breast, ovarian and colorectal cancer each year. The American Lung Association reports that while lung cancer rates have risen by 79% for women over the last 44 years, they decreased by 43% for men. And for the first time in history, there are more young women than men diagnosed with lung cancer.

    News about Pope Leo XIV’s lung cancer diagnosis on Oct. 13, 2026, sparked discussion about increasing rates of the disease among people who have never smoked. Leo reportedly is not a smoker. Potential causes for the disease include environmental exposures and genetics, and recognizing the diverse factors that can increase someone’s risk of lung cancer – regardless of their smoking history – is essential for timely and appropriate screening and treatment.

    Cancer that is found at the earliest stages, like that of the pope, can be treated with surgery and cured for both smokers and nonsmokers. The challenge is that people who have never smoked are not currently included in lung cancer screening guidelines, and tumors are often only found by chance.

    As a thoracic oncologist, I have seen many younger women and never smokers walk into my clinic with a new diagnosis of lung cancer. Particularly for never smokers, lung cancer is unexpected for both patients and their doctors, which can often lead to delays in diagnosis. Researchers have described this trend of increasing lung cancer rates among women in different parts of the world and are starting to understand why cases are on the rise.

    Lung cancer in women

    The first explanation of why rates of lung cancer in women have increased is that many started smoking later than men, pushing back their peak in smoking-related lung cancer diagnoses.

    Women also started smoking in the years when filtered cigarettes were most commonly used. This led to an increased risk of a type of cancer called adenocarcinoma due to the way cigarette filters distribute tobacco smoke to the outer parts of the lungs. Some studies suggest that women are more susceptible to the carcinogenic effects of exposure to tobacco and cigarette smoke, including second-hand smoke, and may develop lung cancer after fewer years of smoking compared to men.

    However, it is important to note that most people diagnosed today with lung cancer are not active smokers. About 20% of women with lung cancer have never smoked – higher than for men with lung cancer who’ve never smoked.

    Watch on  YouTube
    An increasing number of lung cancer diagnoses are among people who never smoked.

    Lung cancer risk factors

    Besides smoking and secondhand smoke, there are several other lung cancer risk factors. These include a family history of cancer and exposure to asbestos, radon and air pollution.

    Exposure to carcinogens in the workplace in the form of inhaled chemicals such as arsenic, beryllium, cadmium, silica and nickel is still a concern in some parts of the world. The potential lung cancer risk of e-cigarette and marijuana smoke is still under study but of potential concern.

    Recently, researchers have also found that genetics can play a role in lung cancer risk in some patients with a strong history of lung cancer. Studies of these families have helped identify potential susceptibility genes for lung cancer and environmental risk factors.

    Like BRCA1 and BRCA2 in breast cancer, alterations in genes that promote or protect against tumor development can contribute to lung cancer development. Researchers have yet to identify specific mutations that may predispose individuals to lung cancer. However, studying familial genetic predispositions can help elucidate how lung cancer develops and lead to new biomarkers for early cancer detection in high-risk groups.

    Lung cancer screening

    In 2021, the United States Preventive Services Task Force updated its lung cancer screening guidelines to include younger patients with less smoking history. Now, lung cancer screening is recommended for adults ages 50 to 80 who have smoked at least one pack per day for 20 years, current smokers and former smokers who quit smoking within the last 15 years. Women at risk for lung cancer can talk to their doctors about ordering a low-dose CT scan for lung cancer screening.

    Nationwide, more than 70% of eligible women undergo breast cancer screening but less than 6% of all eligible smokers pursue lung cancer screening. Researchers estimate that these new screening guidelines will increase the number of women eligible for lung cancer screening by 40% by including those at a younger age who have less smoking exposure.

    CT scan of lung adenocarcinoma
    A low-dose CT scan can help with early detection of lung cancer. In this image, the tumor is the white nodule in the upper right corner of the black space. Atlas of Pulmonary Pathology/Flickr, CC BY-SA

    Lung cancer diagnosis

    In recent years, increasing understanding of the genetic changes that can lead to cancer and how to harness the immune system to treat cancer has led to new targeted therapies and immunotherapies that have improved the prognosis of patients with lung cancer. Women tend to have a better lung cancer prognosis than men, especially if they never smoked and have tumors with molecular changes that can be treated with targeted therapies.

    However, lung cancer symptoms may go unrecognized in women. Symptoms of lung cancer can include coughing, shortness of breath, overwhelming fatigue and pain in the back, chest or shoulder, which could be confused for other ailments. Because women tend to be slightly younger when diagnosed than men, patients may be able to tolerate symptoms longer and delay seeking medical attention. Physicians also might not attribute these symptoms to lung cancer due to a patient’s younger age.

    Recognizing the early symptoms of lung cancer, expanding lung cancer screening eligibility and testing for genetic biomarkers to select the best therapy are some of the steps that could help address the global epidemic of lung cancer in women.

    This is an updated version of an article published on Feb. 1, 2023.

    Estelamari Rodriguez, Associate Director of Community Outreach in Thoracic Oncology, University of Miami

    This article originally appeared on The Conversation. You can read it here.

Explore More Health Stories

Health

Why does your brain mix up memories? A new study examines how memories are misplaced in your brain’s filing cabinets

Health

Getting outside despite your 9‑to‑5 job can improve your mental health – here’s how to spend time in nature during and around working hours

Research

New Russian research suggests that the human lifespan could be up to 156 years

Health

Screen time guidelines for kids and adolescents have shifted as research paints a more nuanced picture